Conditions · Low back pain · Portland & Vancouver
Your back isn't the problem. It's the part that's complaining.
If you've had low back pain for any length of time, someone has probably told you to rest, to stretch, to strengthen your core, to lose weight, or to live with it. The pain came back anyway.
Two-hour first visit · one-on-one with the doctor every visit

Sound familiar?
Where low back pain usually shows up
What we see
The spine is doing the hips' job.
In our clinical experience, low back pain almost always comes from a pattern, not a single injury. The back works too hard because something else has stopped working: the hips, the glutes, the breath, the brace.
The most common pattern we see is a body that's overusing the spine and underusing the hips. The glutes and hamstrings — the muscles built for hinging, lifting, and load-bearing — go quiet, and the small muscles around the spine try to make up the difference. They can't.
Over time the spine takes more load than it was designed for, the tissues get irritated, and the nervous system turns up the volume on the pain signal. That's why "fixing the back" by treating the back rarely works for long.
How we evaluate · The Movement Paradigm
We watch how you breathe, brace and hinge.
Every first visit scores the same three patterns. Here's what we usually find with low back pain.

Breathe
Shallow chest breathing instead of diaphragmatic breathing. The back muscles end up doing what the diaphragm should be doing, and they stay tight.

Brace
Midline stability that depends on stiffening the spine rather than pressurizing through breath. The result is excessive spinal load on every step, every lift, every cough.

Hinge
Bending from the back instead of the hips. Efficient movement comes from the glutes and hamstrings; when they're not doing their share, the spine pays.
Most common in low back painWhat happens when you book
A clear path, from your first visit forward.
The first visit
Two full hours, one-on-one with the doctor. Movement screen, pattern scoring, and a plan built around what your body actually does - not what a template says it should.
Six-visit plan
Adjustments, soft-tissue work, and pattern retraining. Same doctor each time. Same room. Visible progress that you can feel between visits.
Re-exam & next steps
At visit six we re-score the patterns and decide together - maintain, taper, or refer out. If we're not the right fit, we'll point you to who is.
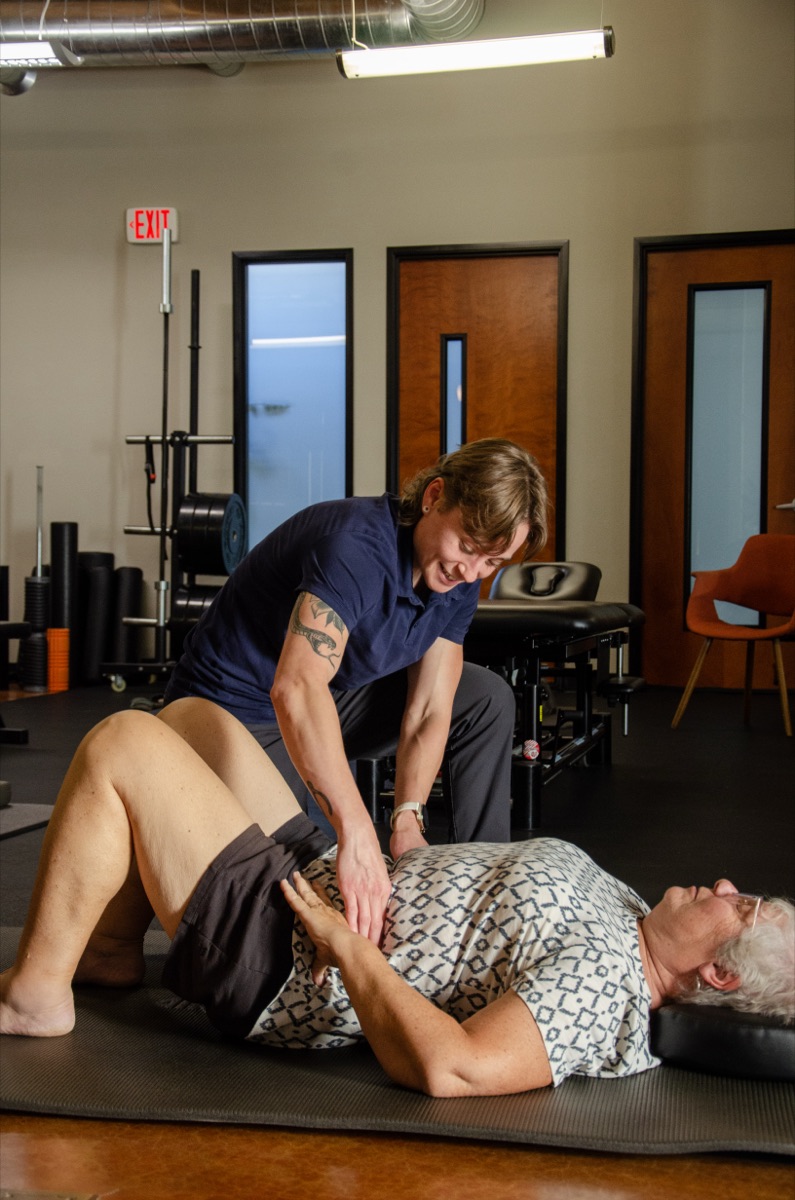
How we treat low back pain
Retrain the pattern so the back stops compensating.
What treatment looks like depends on what we find in the evaluation, but it's almost always a combination of:
- 1Movement retrainingBuilding the breath, brace, and hinge patterns that are missing, so the back stops compensating.
- 2Targeted strengtheningUsually glutes, hamstrings, and the bracing system, so the new patterns hold.
- 3Spinal manipulative therapyChiropractic adjusting where it helps the nervous system reset, not as a stand-alone fix.
- 4Soft tissue workReleasing the tissues that have been holding the compensation.
Some patients need more than what's offered in our clinic. We work with a multidisciplinary network — acupuncturists, massage therapists, MDs, imaging centers — and refer out when that's the right call.
Why it’s not too late
Most of the people we see for low back pain have had it for years. Movement patterns are habits, and habits can be rebuilt at any age — they just need consistent input. What we don’t do is hand you a generic exercise sheet and send you home; the retraining is specific to the patterns we find in your evaluation, and you’ll practice them with us until they feel automatic.
If you’re carrying a back that’s hurt for a long time, you haven’t missed your window.

Ask the doctor
How can I get relief from lower back pain?
Lower back pain comes down to how you stabilize under load — and why one spot takes it. Dr. Zach on finding your pattern instead of resting, and why that's what actually gives relief.
Read Dr. Zach's answer →I started seeing Dr. Zach Cullen at Move Better a few weeks ago for chronic neck and back pain, and the experience has been completely different from any chiropractor or PT I've worked with before.
What the research says
We show our evidence.
No guideline names our method, but the pieces line up with what the major reviews and guidelines support: Tap a card for the details and the source.
Stay active, don't rest it out. The Lancet, 2018
The Lancet's 2018 review of back pain guidelines found they agree on education, getting back to normal activity, and exercise first — and that rest is used far more than the evidence supports. The Lancet, 2018 ↗
Exercise has the strongest evidence. Cochrane, 2021
A Cochrane review of 249 trials found exercise probably eases chronic low back pain more than no treatment or usual care — by about 15 points on a 100-point pain scale, which the authors count as a meaningful difference. The gain in day-to-day function was smaller. Against other conservative care the differences were small, and against manual therapy there was no difference. Cochrane, 2021 ↗
Spinal manipulation performs about as well as other recommended care — not better. BMJ, 2019 · JAMA, 2017
For chronic pain, a BMJ review of 47 trials found manipulation or mobilisation worked about as well as other recommended treatments such as exercise. Reported side effects were mostly short-lived soreness or stiffness, mild to moderate, but only about half the trials tracked them, and rare serious reactions cannot be ruled out. For recent-onset pain, a JAMA review of 26 trials found moderate-quality evidence of a modest improvement in pain and function over the first six weeks. No serious side effects were linked to manipulation in those trials, though most did not track side effects. BMJ, 2019 ↗JAMA, 2017 ↗
Manual therapy alongside exercise, not alone. NICE NG59
The UK's NICE guideline says to consider manual therapy, including spinal manipulation, only as part of a package that includes exercise. NICE NG59 ↗
Guidelines list manipulation as an option, not a cure. American College of Physicians, 2017
The American College of Physicians includes it among its recommended non-drug options, rates that evidence as low-quality, and notes that most acute episodes improve over time regardless of treatment. American College of Physicians, 2017 ↗
Exercise lowers the chance of another episode. JAMA Internal Medicine, 2016 · abstract
A review found exercise, alone or with education, lowers the risk of a new episode of low back pain; education alone, back belts and shoe insoles did not. JAMA Internal Medicine, 2016 · abstract ↗
That's why we pair manipulation with movement retraining instead of offering it alone.
Other conditions
What else we work with.
- Headaches & migrainesThe pain shows up in your head, but the source is usually the neck, shoulders, and breath. We work upstream of the symptom.
- Shoulder painMost shoulders hurt because the shoulder blade isn't doing its job. The fix is teaching it to move again — not just adjusting the joint that's complaining.
- Knee painIn our experience, knee pain rarely starts in the knee. It usually starts at the hip or the ankle, and the knee — stuck in the middle — pays for it.
- Foot & ankle painYour feet are the foundation of everything above them. When they don't load well, the rest of the body compensates.
First visits are 2 hours, one-on-one with a doctor.
We'll evaluate how you move, talk through what we see, and tell you whether we can help — or refer you out if we can't.